Epilepsy Semiology, EEG Interpretation, Clinical Approach & 10-20 Localization
Evidence-based localization from bedside ictal/postictal semiology to bipolar phase reversals, cortical dipoles, benign EEG variants, and acute vs unprovoked seizure workup.
Visual Infographic: คนในท่าชักต่างๆ ตาม Semiology & Lateralization (6 ท่ามาตรฐาน)
Interactive Body Atlasสลับซีกสมองที่เป็นจุดกำเนิดชัก (Left vs Right Hemisphere Focus) เพื่อดูทิศทางแขน ขา หน้า และตาของผู้ป่วยในแต่ละท่าชักแบบอัตโนมัติ
1. ท่านักฟันดาบ (Fencing Posture / M2e Sign)
Fencing Posture (M2e Sign — SSMA Seizure)
แขนข้างที่ยกกางออกและงอศอก 90° (Abduction + External Rotation + Elbow Flexion) พร้อมหันหน้าและตามองมือข้างที่ยก จะอยู่ "ฝั่งตรงข้าม (Contralateral)" กับจุดกำเนิดชัก ส่วนแขนข้างเดียวกับรอยโรคจะเหยียดลง
จุดชักที่ Left SSMA → แขนขวายกตั้งท่าฟันดาบ + หน้าและตาหันมองมือขวา + แขนซ้ายเหยียดตรงลงข้างลำตัว (รู้ตัวดี/เกิดขึ้นสั้นๆ 10–30 วินาทีขณะหลับ)
- 1.Contralateral Arm: Shoulder abducted 90°, externally rotated, elbow flexed ("มองมือที่ยก")
- 2.Ipsilateral Arm: Extended downward/backward
- 3.Preserved Awareness: ผู้ป่วยมักยังรู้สึกตัวแต่พูดไม่ออก (Tonic vocalization/speech arrest) หยุดชักปุ๊บตื่นดีทันที
โปสเตอร์ภาพคนในท่าชักทั้ง 6 รูปแบบตาม Semiology & Cortical Lateralization
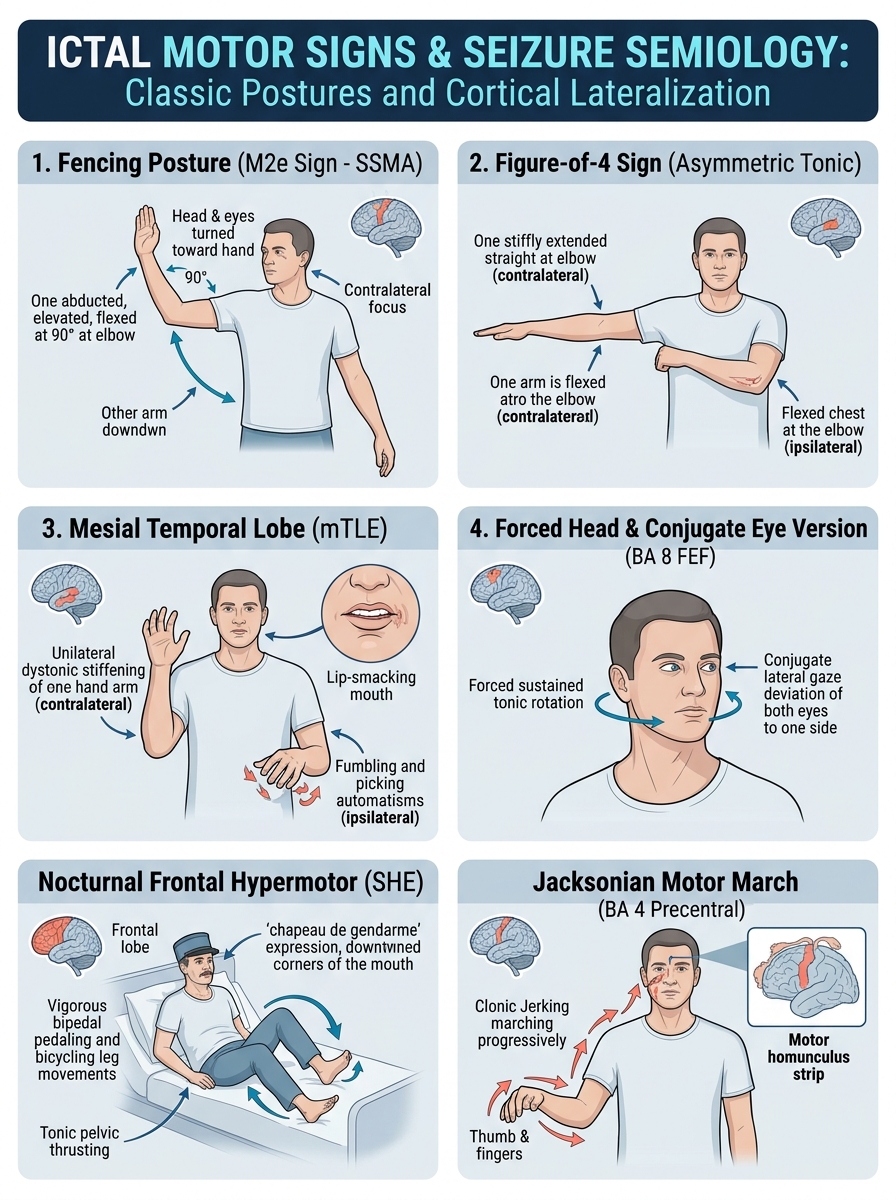
1. ท่านักฟันดาบ (Fencing Posture / M2e Sign)
Fencing Posture (M2e Sign — SSMA Seizure)
2. ท่าเลขสี่ (Figure-of-4 Sign)
Figure-of-4 Asymmetric Tonic Posturing
3. มือเกร็งบิดครึ่งซีก + มืออีกข้างหยิบจับอัตโนมัติ (mTLE)
Unilateral Dystonic Posturing + Ipsilateral Manual Automatisms
4. หน้าและตาบิดเกร็งหันค้าง (Forced Head & Eye Version)
Forced Conjugate Head & Eye Version + Facial Clonic
5. ชักถีบขาปั่นจักรยานขณะหลับ + ปากคว่ำ (Frontal Hypermotor & Chapeau de Gendarme)
Sleep-Related Hypermotor Bicycling & Ictal Pouting
6. กระตุกลามตามลำดับแผนที่สมอง (Jacksonian Motor March & Todd’s Paresis)
Jacksonian Clonic March & Postictal Todd’s Paralysis
Interactive Bedside Semiology Lateralizer & Localizer
Select an observed ictal or postictal clinical sign and body side to compute the lateralized hemisphere and cortical zone
Because "Forced Head & Eye Version (Sustained, Unnatural)" is a CONTRALATERAL lateralizing sign (>90% Contralateral (especially when occurring right before FBTCS generalization)) and was observed on the Right side of the body, the seizure onset / propagation zone localizes to the LEFT Hemisphere (Frontal (FEF BA 8) or Temporal propagation).
Cortical Lobe-by-Lobe Seizure Semiology & Propagation Atlas
Detailed functional anatomy, subjective auras, motor/autonomic signatures, and propagation pathways across all 5 cerebral lobes
Mesial Temporal Lobe (mTLE — Amygdala, Hippocampus, Parahippocampal Gyrus)
Anatomical Network: Hippocampal sclerosis (HS), amygdala, entorhinal cortex (limbic network)
- •Ascending epigastric sensation ("butterflies" or rising warmth from stomach to throat — most common)
- •Experiential / psychic phenomena: Déjà vu, jamais vu, dreamy state, depersonalization
- •Affective aura: Intense unprovoked fear/panic (amygdala), rarely ictal pleasure/ecstasy
- •Olfactory aura (uncinate fits — unpleasant burning rubber/fecal odor) or gustatory (metallic/bitter taste)
- •Behavioral arrest / motionless stare with impaired awareness (focal impaired awareness seizure)
- •Oroalimentary automatisms: Lip smacking, chewing, swallowing, tooth grinding
- •Ipsilateral manual automatisms: Fumbling, picking at clothes, pill-rolling ("sign of the bedsheet")
- •Contralateral upper limb dystonic posturing (due to propagation to ipsilateral basal ganglia)
- •Postictal ipsilateral nose-wiping (performed by the non-paretic ipsilateral hand)
- •Ictal tachycardia (>90% of mTLE), flushing or pallor, mydriasis
- •Ictal spitting, ictal vomiting, or ictal urinary urge (typically non-dominant / right temporal)
- •Pilomotor erection ("goosebumps" — often ipsilateral or unilateral in autoimmune/limbic encephalitis)
Postictal & Duration: Typically 60–120 seconds (1–2 min). Prolonged postictal confusion (5–20+ min) and postictal aphasia if dominant hemisphere.
Spread: Slow propagation via fornix, cingulum, and uncinate fasciculus to ipsilateral insula, basal ganglia, and frontal lobe.
Lateral / Neocortical Temporal Lobe (nTLE — Superior/Middle/Inferior Temporal Gyri)
Anatomical Network: Heschl gyrus (A1), Wernicke area (posterior STG), temporo-parieto-occipital junction
- •Auditory aura: Elementary buzzing, ringing, humming, or clicks (Heschl gyrus); or complex music/voices (association cortex)
- •Vertiginous aura: True rotational vertigo or disequilibrium (temporo-parietal junction / vestibular cortex)
- •Complex visual hallucinations or illusions (macropsia/micropsia) without elementary flashes
- •Less frequent epigastric aura compared to mTLE
- •Early aphasic / dysphasic seizure (Wernicke receptive aphasia or global speech arrest in dominant hemisphere)
- •Faster loss of awareness and earlier head/eye version than mTLE
- •Rapid facial clonic twitching and earlier progression to bilateral tonic-clonic (FBTCS) within 30–60 sec
- •Fewer oroalimentary automatisms unless discharge propagates medially into the amygdala/hippocampus
Postictal & Duration: Shorter than mTLE (30–90 seconds) with more rapid secondary generalization and prominent postictal receptive aphasia (dominant).
Spread: Rapid propagation via arcuate fasciculus to perisylvian/frontal operculum and contralateral hemisphere.
- ✓Combination of ipsilateral manual automatisms + contralateral dystonic arm posturing has >95% PPV for lateralizing the seizure onset zone.
- ✓Ictal speech preservation (fluent, meaningful speech during automatisms) strongly favors the NON-DOMINANT (usually right) temporal lobe.
- ✓Postictal dysphasia/aphasia (tested by naming objects immediately after the seizure) is one of the most reliable signs of DOMINANT temporal lobe involvement.
- !Insular or orbitofrontal seizures can mimic mTLE completely once they propagate to the mesial temporal structures.
- !Bitemporal propagation can cause bilateral manual automatisms, masking the initial lateralizing dystonia.